
Volume 22, Issue 4 (12-2025)
J Res Dev Nurs Midw 2025, 22(4): 52-57 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Kool S, Soheily A, Domaradzki J, Jahanshahi R, Sanagoo A, Jouybari L. Organizational climate and presenteeism orientation in nurses: A cross-sectional study. J Res Dev Nurs Midw 2025; 22 (4) :52-57
URL: http://nmj.goums.ac.ir/article-1-2144-en.html
URL: http://nmj.goums.ac.ir/article-1-2144-en.html
Shahrbanoo Kool1 

 , Ali Soheily2 , Jan Domaradzki3 , Reza Jahanshahi4 , Akram Sanagoo5 , Leila Jouybari5
1- School of Paramedical Sciences, Golestan University of Medical Sciences, Gorgan, Iran
2- Hazrat Rasoul Akram Hospital, Golestan University of Medical Sciences, Kalaleh, Iran
3- Department of Social Sciences and Humanities, Poznan University of Medical Sciences, Poznan, Poland
4- Student Research Committee, Golestan University of Medical Sciences, Gorgan, Iran ,rjahanshahi75@yahoo.com
5- Faculty of Nursing and Midwifery, Golestan University of Medical Sciences, Gorgan, Iran
2- Hazrat Rasoul Akram Hospital, Golestan University of Medical Sciences, Kalaleh, Iran
3- Department of Social Sciences and Humanities, Poznan University of Medical Sciences, Poznan, Poland
4- Student Research Committee, Golestan University of Medical Sciences, Gorgan, Iran ,
5- Faculty of Nursing and Midwifery, Golestan University of Medical Sciences, Gorgan, Iran
Full-Text [PDF 566 kb]
(1281 Downloads)
| Abstract (HTML) (4218 Views)
Discussion
Organizational climate and presenteeism among nurses in this study were reported at moderate levels. The present study found that higher organizational climate scores were associated with lower levels of nurse presenteeism. In other words, each one-unit increase in the overall organizational climate score predicted an approximately 0.5% reduction in nurses’ presenteeism, although the effect size was small. This finding is consistent with several studies. Jing et al. (2026), in an international longitudinal study, showed that ethical leadership had a reducing effect on nurse presenteeism and that part of this relationship was mediated by organizational climate and professional identity (25). Mansour et al. (2022) found that psychological safety climate (One facet of organizational climate) significantly reduced presenteeism in nurses by attenuating the intensity of workload (26). Wang et al. (2024) reported that the greater the perceived organizational support (POS) among nurses, the lower the frequency of presenteeism and its associated harms (27).
In this study, nurses assigned the highest organizational-climate scores to the dimensions of “Intimacy” and “team spirit,” which reflects the importance of close interpersonal relationships and team cohesion in the nursing work environment (28). Organizational intimacy, defined as the proximity, solidarity, and tendency of team members to be together, has been shown to be associated with increased team participation, positive organizational behavior, and job satisfaction (29). Moreover, studies indicate that work settings in which nurses feel supported, valued, and perceive organizational attention to their participation and welfare lead to improved job satisfaction and better mental health among nurses (14,30). Consistent with these findings, a positive perception of working conditions (Including work-life balance and coworker support) can help prevent stress-induced presenteeism in nurses. In addition, reviews of positive nursing work environments have identified the “communication climate (Team spirit)” as one of the key components of the workplace (31).
Mohammadi et al., in a qualitative study in Iran, examined the notion of “nurses without a nurse,” showing that when the organizational climate is not support-oriented, managers may neglect to acknowledge the necessity of nurses’ attendance when ill. Nurses reported that managers sometimes tell them, “We cannot sacrifice patients because of your absence; you are a nurse and must be at your post!” This kind of undermining organizational climate, where managers encourage physical attendance even under adverse conditions, is a clear manifestation of presenteeism (32). Overall, a favorable organizational climate, by fostering a sense of belonging and mutual support among staff, reduces undesirable behaviors such as presenteeism (26). Moreover, a recent systematic review by Gerlach et al. (2024) emphasized that improving working conditions and promoting a supportive organizational culture and effective management can mitigate the negative effects of presenteeism among nurses (33).
In short, the broader body of evidence indicates a negative relationship between the quality of organizational climate and the prevalence of presenteeism, a pattern that is echoed across multiple contemporary studies. From the perspective of Social Exchange Theory, when employees perceive that the organization cares for and supports their well-being, they reciprocate with loyalty and a sense of responsibility; thus, high organizational support can strengthen commitment in ways that manifest as positive work behaviors such as reduced presenteeism (34,35). Likewise, according to Conservation of Resources theory, a positive organizational climate (Especially one characterized by psychological safety) constitutes an important job resource that helps employees preserve their psychological and physical resources and prevents fatigue or occupational burnout. Shafiee Sabet et al. (2023) reported that most nurses did not perceive their shift schedules as aligned with their preferences and recommended that managers take steps to reduce presenteeism and enhance nurses’ resilience (19). Mansour et al. (2022), drawing on the same theoretical perspective, showed that a psychological safety climate, by reducing job stressors, increases nurses’ capacity to cope with heavy workloads and thereby prevents presenteeism (26).
This is one of the first studies to examine organizational climate and presenteeism among nurses in Iran. The present study has several important strengths, including an adequate sample size (n = 327) and a favorable response rate (81.3%), use of standardized and locally validated questionnaires with reported reliability, adherence to STROBE reporting guidelines, and rigorous statistical analyses, such as logarithmic transformation to normalize the presenteeism variable, along with diagnostic model checks and control of multiple background covariates, all of which contribute to the study’s internal validity.
Nevertheless, several limitations must be acknowledged when interpreting our findings. First, the cross-sectional design precludes causal inference. Second, convenience sampling from a limited number of centers and the web-based distribution may produce a local/selection bias and limit generalizability to other regions or to nurses with lower digital access or different working conditions. Third, exclusive reliance on self-report measures increases the risk of common-method variance, recall error, and social-desirability bias. Fourth, the regression model accounted for only a small proportion of the variance in presenteeism (Adjusted R² = 0.078), indicating that the included predictors-mainly demographic and organizational climate variables-were not strong determinants of presenteeism. This suggests that additional organizational and job-related factors (e.g., workload, shift patterns, or staffing adequacy) likely play a more substantial role and should be examined in future research. Taken together, these limitations argue for cautious interpretation of the results.
Based on the findings of this study, future research should explore the causal relationship between organizational climate and presenteeism using longitudinal or experimental designs. It is recommended that future studies examine potential mediating and moderating variables such as perceived organizational support, individual resilience, and organizational commitment to better understand the mechanisms linking climate to presenteeism.
Conclusion
The present study found that a more positive organizational climate was associated with lower levels of presenteeism among nurses, although the effect size was modest. These findings suggest actionable managerial strategies that healthcare organizations can adopt to mitigate presenteeism and improve care quality, for example, flexible scheduling and self-rostering, ensuring adequate staffing and equitable workload redistribution, implementing employee psychological-support services, training managers in supportive leadership and conflict resolution, and establishing formal peer-support and clear absence policies.
Acknowledgement
This study was approved by the Student Research Committee of Golestan University of Medical Sciences. The authors thank the Vice-Chancellor for Research and Technology of Golestan University of Medical Sciences for their support.
Funding sources
None.
Ethical statement
The study protocol was approved by the Ethical Review Board of Golestan University of Medical Sciences (IR.GOUMS.REC.1404.224). The study was conducted in accordance with the principles of the Declaration of Helsinki. All participants provided written informed consent after being informed about the study aims, procedures, potential risks, and benefits. Participation was voluntary; participants were explicitly informed that they could refuse to participate or withdraw at any time without penalty or loss of benefits to which they were otherwise entitled. Participant confidentiality was maintained: Data were anonymized/coded and stored securely with access restricted to authorized study personnel.
Conflicts of interest
None.
Author contributions
S. K. and R. J.: Conceptualization; S. K., L. J., A. S., and R. J.: Methodology; A. S. and S. K.: Resources; R. J. and S. K.: Writing-Original draft preparation; J. D. and R. J.: Writing-Review and Editing; L. J. and A. S.: Supervision; R. J.: Project administration.
Data availability statement
All data analyzed during this study are included in this published article. Additional de-identified participant-level data may be made available from the corresponding author upon reasonable request, subject to review and approval by the study authors and applicable institutional policies.
Use of Artificial Intelligence
The authors acknowledge the contribution of ChatGPT (OpenAI) in translating and paraphrasing portions of this manuscript.
Full-Text: (823 Views)
Introduction
Organizational climate is defined as employees’ perceptions and interpretations of their work environment and organizational characteristics, which directly affect their behaviors, attitudes, and job performance (1). This concept is of vital importance in healthcare and hospital settings, as the quality of care and medical services is directly influenced by the prevailing organizational climate (2). Research has shown that organizational climate can both stimulate positive job behaviors, such as increased organizational commitment, improved performance, and extra-role behaviors, and at the same time foster negative outcomes, including increased absenteeism and heightened job stress (3-5).
Among different professions, nursing is particularly susceptible to the effects of organizational climate due to its highly sensitive and stressful nature. Nurses, who constitute the largest professional group in healthcare systems (40 - 60% of the workforce in medical universities), play a pivotal role in the delivery of health services (6). Studies indicate that factors such as high workload, staff shortages, insufficient salary and benefits, inequitable distribution of work shifts, and lack of managerial support can weaken the organizational climate in nursing wards (7,8). Conversely, a positive organizational climate characterized by fairness, managerial support, employee participation in decision-making, and constructive communication can lead to higher job satisfaction, stronger organizational commitment, and improved performance among nurses (5,6,9).
One of the most important consequences of an unfavorable organizational climate in nursing settings is “presenteeism.” Presenteeism refers to situations in which employees attend work despite illness, fatigue, or reduced capacity, but fail to perform at their expected level (10,11). This phenomenon is highly prevalent among nurses, with studies reporting that between 60% and 90% of nurses experience presenteeism at least once during their career (12,13). At the organizational level, presenteeism is associated with lower quality of patient care, increased medical and nursing errors, reduced productivity, and higher healthcare costs (13-15). Some studies have even suggested that the detrimental impact of presenteeism may be up to three times greater than absenteeism (16).
Despite the importance of this issue, few studies in Iran have examined the relationship between organizational climate and presenteeism in healthcare settings (17,18). Given that cultural and organizational factors unique to each country can influence this relationship, the Iranian context (With its emphasis on responsibility and self-sacrifice) may contribute to higher levels of presenteeism among nurses. Additionally, specific challenges within the Iranian healthcare system, such as workforce shortages, high workload, and limited resources, may further affect this relationship. For instance, Shafiei Sabet et al. (2023) found a significant association between presenteeism and resilience among 300 nurses in intensive care units in Tehran, while shift scheduling was not aligned with nurses’ preferences (19).
The findings are expected to inform managerial decision-making by identifying organizational levers that may reduce presenteeism, for example, enhancing managerial support, establishing comprehensive staff-support systems, ensuring equitable shift allocation, improving working conditions, and promoting nurses’ mental health. Moreover, by addressing a relative paucity of empirical evidence from Iranian healthcare settings, this study contributes to the literature and provides a basis for future research in other clinical contexts. Therefore, this study aimed to examine the association between organizational climate and presenteeism among Iranian nurses.
Methods
Study design
This cross-sectional study was conducted in 2025 among nurses working in selected educational and medical centers affiliated with Golestan University of Medical Sciences, Iran. The STROBE checklist was followed for reporting in the study (20).
Participants and sampling
The study population comprised nurses working in selected educational and medical centers affiliated with Golestan University of Medical Sciences [Panj Azar, Shahid Sayad Shirazi, Hazrat Rasool Akram (PBUH), Kalaleh, and Payambar Azam hospitals]. Participants were recruited by convenience sampling. An online questionnaire link was distributed to eligible nurses, and participation was voluntary. In total, 412 nurses received the survey link, 335 responses were returned (Response rate: 81.3%), eight questionnaires were excluded because they were incomplete, and the final analytic sample comprised 327 participants.
Eligible participants met the following inclusion criteria: (1) Willingness to participate and provision of informed consent, (2) a minimum academic qualification of Bachelor of Science in Nursing, (3) at least six months of clinical work experience at the hospitals, and (4) access to the Internet and a smartphone. The exclusion criteria were self-reported current psychiatric disorders and self-reported use of psychotropic medications within the past six months.
Sample size calculation
Based on the parameters reported by Pavlović et al. (2022) (21) and following Cohen’s guidelines, the required sample size for this study was determined using G*Power (Version 3.1) based on an a priori power analysis. Assuming a small-to-medium effect size (𝑓2 = 0.1), a significance level of 𝛼 = 0.05, and a desired statistical power of 0.99, with 7 predictors in the model, the calculated minimum sample size was 300 participants. A 10% attrition rate was also considered in estimating the final sample size. The achieved sample (n = 327) met this requirement (22).
Survey instrument
Data were collected using a demographic and occupational characteristics form and two standardized questionnaires: The Halpin and Croft Organizational Climate Questionnaire and the Presenteeism in Nursing Questionnaire.
Demographic and occupational characteristics form this study-specific form comprised two sections. The first section recorded sociodemographic information including age, gender, marital status, place of residence, and medical history. The second section collected occupational characteristics, including educational level and years of work experience.
Halpin and croft organizational climate questionnaire
Organizational climate was measured using the Halpin and Croft questionnaire (1963), which contains 32 items scored on a five-point Likert scale (1 = very low, 2 = low, 3 = moderate, 4 = high, 5 = very high). Item scores are summed to yield subscale scores and a total score.
Each of the eight subscales comprises four items (Possible subscale range = 4 - 20), and the total organizational climate score ranges from 32 to 160. The questionnaire assesses the following dimensions: Team spirit (Items 1 - 4), harassment (Items 5 - 8), intimacy (Items 9 - 12), interest (Items 13 - 16), consideration (Items 17 - 20), distancing (Items 21 - 24), influence and dynamics (Items 25 - 28), and focus on production (Items 29 - 32). Higher scores indicate a stronger perception of the corresponding climate dimension and a more positive overall organizational climate (22). The instrument has demonstrated excellent reliability and validity in Iranian healthcare settings; for example, studies among emergency medical staff reported Cronbach’s α = 0.966 and composite reliability = 0.968 (23), while other researchers have reported overall α = 0.78 (24).
Presenteeism in nursing questionnaire
Presenteeism was assessed using the 17-item presenteeism questionnaire developed and validated by Mohammadi et al. Items are rated on a five-point Likert scale (1 = never, 2 = rarely, 3 = sometimes, 4 = often, 5 = always). The instrument comprises three subscales: Incomplete cognitive presence (Items 1 - 8; range 8 - 40), incomplete emotional presence (Items 9 - 12; range 4 - 20), and incomplete behavioral presence (Items 13 - 17; range 5 - 25). Subscale scores are summed to produce a total presenteeism score (Range 17 - 85), with higher scores reflecting greater levels of presenteeism. The questionnaire’s internal consistency has been reported as acceptable (Cronbach’s α > 0.80), and content validity was confirmed by the original developers (25).
Data collection
After obtaining the necessary approvals, the questionnaire and the informed-consent form were prepared and administered electronically via Porsline (An Iranian online survey platform). The online questionnaire link was distributed through professional workgroups on Telegram and WhatsApp and the Persian app, which were used by nurses working in the selected hospitals. Participants were identified through their membership in these hospital-specific virtual groups, where the survey link and study information were posted with an invitation to participate voluntarily. Before accessing the questionnaire items, participants viewed an introductory page describing the study’s aims, ethical considerations, and confidentiality assurance. Those who agreed to participate indicated their informed consent by continuing to the questionnaire. The mean completion time per questionnaire was approximately 30 minutes. To ensure data completeness, the online questionnaire was configured with mandatory response settings for all items. Consequently, no incomplete questionnaires were collected, and no missing data imputation was necessary.
Data analysis
Descriptive statistics were computed for all study variables. Continuous variables are presented as mean ± standard deviation (SD) and median (Interquartile range, IQR) as appropriate; categorical variables are reported as frequencies and percentages. Normality of continuous variables was assessed by visual inspection of histograms and Q-Q plots and formally tested using the Shapiro - Wilk test. Because the presenteeism score was negatively skewed, the variable was natural-log transformed (Log-presenteeism) to approximate normality and stabilize variance prior to regression analyses. After log transformation, skewness (-0.317; SE = 0.136; SES = -2.34) and kurtosis (0.181; SE = 0.271; SES = 0.67) indicated a nearly symmetric and approximately normal distribution.
For data analysis, independent samples t-tests, Mann-Whitney U tests, and Pearson’s and Spearman’s correlation analyses were used as appropriate. In multivariable linear regression, all covariates identified as theoretically relevant (Age, gender, education, marital status, place of residence, and medical history) were entered simultaneously using the enter method. This approach was chosen to avoid model instability associated with automated stepwise procedures and to ensure inclusion of conceptually justified variables. Work experience was excluded from multivariable regression due to a high degree of collinearity with age. Because age and work experience were highly correlated (R = 0.87), age was retained as it theoretically reflects both biological and career-related influences on presenteeism.
Prior to conducting regression analyses, the assumptions of linearity, homoscedasticity, absence of multicollinearity, and lack of influential cases were assessed. Collinearity among independent variables was evaluated in two steps. First, pairwise correlations between continuous independent variables were examined using Spearman’s correlation coefficients. Second, multicollinearity diagnostics were performed by calculating the Variance Inflation Factor (VIF) for each predictor. All VIF values ranged between 1.00 and 1.30, indicating no multicollinearity issues. Model assumptions were further examined through standardized residuals and Cook’s distance, confirming that all assumptions were met.
All tests were two-tailed, and a P-value < 0.05 was considered statistically significant. Analyses were performed using IBM SPSS Statistics version 26.
Results
In the present study, the mean age of participants was 33.91 ± 6.75 years and their mean work experience was 9.56 ± 6.30 years. The majority of participating nurses were female (52.6%) and married (61.5%). Table 1 presents the demographic characteristics of the participants along with the comparison of organizational climate and presenteeism scores across sociodemographic subgroups.
Pearson’s correlation analysis (Performed on log-transformed presenteeism scores to correct for non-normality) indicated a positive correlation between organizational climate and nurses’ age (R = 0.152, P-value = 0.006), while no significant correlation was observed with work experience (R = 0.084, P-value = 0.128). Moreover, log-transformed presenteeism was positively correlated with nurses’ age (R = 0.125, P-value = 0.024) but not with work experience (P > 0.05).
Correlation between organizational climate and presenteeism orientation scale score
Cronbach’s alpha for the Organizational Climate scale was α = 0.72 and for the Presenteeism scale α = 0.84, both exceeding the conventional threshold of 0.70, indicating acceptable to good internal consistency. Spearman’s correlation analysis revealed a weak but statistically significant negative correlation between organizational climate and nurses’ presenteeism (rs = -0.156, P-value = 0.005). Descriptions of the dimensions of the main variables are reported in Table 2.
A multivariable linear regression was performed with log-transformed presenteeism as the dependent variable (n = 327). The overall model was significant (F (7, 319) = 4.93, P < 0.001) and explained 7.8% of the variance in log-presenteeism (R² = 0.098, adjusted R² = .078). Organizational climate was a significant negative predictor of log-presenteeism, while age was a significant positive predictor, indicating that while organizational climate and age were statistically significant predictors, the overall explanatory power of the model was modest. This suggests that other unmeasured factors may play a larger role in predicting nurses’ presenteeism; other covariates were not significant (Table 3). Diagnostics indicated no problematic multicollinearity (VIFs ≈ 1.0), no influential cases (Maximum Cook’s D = 0.057), and standardized residuals within acceptable bounds (Min = -3.89, max = 2.40).
Higher organizational climate scores were independently associated with slightly lower presenteeism (Approximately 0.5% decrease in the original scale per 1-unit increase in organizational climate), while older age was associated with slightly higher presenteeism; effect sizes were small.
Organizational climate is defined as employees’ perceptions and interpretations of their work environment and organizational characteristics, which directly affect their behaviors, attitudes, and job performance (1). This concept is of vital importance in healthcare and hospital settings, as the quality of care and medical services is directly influenced by the prevailing organizational climate (2). Research has shown that organizational climate can both stimulate positive job behaviors, such as increased organizational commitment, improved performance, and extra-role behaviors, and at the same time foster negative outcomes, including increased absenteeism and heightened job stress (3-5).
Among different professions, nursing is particularly susceptible to the effects of organizational climate due to its highly sensitive and stressful nature. Nurses, who constitute the largest professional group in healthcare systems (40 - 60% of the workforce in medical universities), play a pivotal role in the delivery of health services (6). Studies indicate that factors such as high workload, staff shortages, insufficient salary and benefits, inequitable distribution of work shifts, and lack of managerial support can weaken the organizational climate in nursing wards (7,8). Conversely, a positive organizational climate characterized by fairness, managerial support, employee participation in decision-making, and constructive communication can lead to higher job satisfaction, stronger organizational commitment, and improved performance among nurses (5,6,9).
One of the most important consequences of an unfavorable organizational climate in nursing settings is “presenteeism.” Presenteeism refers to situations in which employees attend work despite illness, fatigue, or reduced capacity, but fail to perform at their expected level (10,11). This phenomenon is highly prevalent among nurses, with studies reporting that between 60% and 90% of nurses experience presenteeism at least once during their career (12,13). At the organizational level, presenteeism is associated with lower quality of patient care, increased medical and nursing errors, reduced productivity, and higher healthcare costs (13-15). Some studies have even suggested that the detrimental impact of presenteeism may be up to three times greater than absenteeism (16).
Despite the importance of this issue, few studies in Iran have examined the relationship between organizational climate and presenteeism in healthcare settings (17,18). Given that cultural and organizational factors unique to each country can influence this relationship, the Iranian context (With its emphasis on responsibility and self-sacrifice) may contribute to higher levels of presenteeism among nurses. Additionally, specific challenges within the Iranian healthcare system, such as workforce shortages, high workload, and limited resources, may further affect this relationship. For instance, Shafiei Sabet et al. (2023) found a significant association between presenteeism and resilience among 300 nurses in intensive care units in Tehran, while shift scheduling was not aligned with nurses’ preferences (19).
The findings are expected to inform managerial decision-making by identifying organizational levers that may reduce presenteeism, for example, enhancing managerial support, establishing comprehensive staff-support systems, ensuring equitable shift allocation, improving working conditions, and promoting nurses’ mental health. Moreover, by addressing a relative paucity of empirical evidence from Iranian healthcare settings, this study contributes to the literature and provides a basis for future research in other clinical contexts. Therefore, this study aimed to examine the association between organizational climate and presenteeism among Iranian nurses.
Methods
Study design
This cross-sectional study was conducted in 2025 among nurses working in selected educational and medical centers affiliated with Golestan University of Medical Sciences, Iran. The STROBE checklist was followed for reporting in the study (20).
Participants and sampling
The study population comprised nurses working in selected educational and medical centers affiliated with Golestan University of Medical Sciences [Panj Azar, Shahid Sayad Shirazi, Hazrat Rasool Akram (PBUH), Kalaleh, and Payambar Azam hospitals]. Participants were recruited by convenience sampling. An online questionnaire link was distributed to eligible nurses, and participation was voluntary. In total, 412 nurses received the survey link, 335 responses were returned (Response rate: 81.3%), eight questionnaires were excluded because they were incomplete, and the final analytic sample comprised 327 participants.
Eligible participants met the following inclusion criteria: (1) Willingness to participate and provision of informed consent, (2) a minimum academic qualification of Bachelor of Science in Nursing, (3) at least six months of clinical work experience at the hospitals, and (4) access to the Internet and a smartphone. The exclusion criteria were self-reported current psychiatric disorders and self-reported use of psychotropic medications within the past six months.
Sample size calculation
Based on the parameters reported by Pavlović et al. (2022) (21) and following Cohen’s guidelines, the required sample size for this study was determined using G*Power (Version 3.1) based on an a priori power analysis. Assuming a small-to-medium effect size (𝑓2 = 0.1), a significance level of 𝛼 = 0.05, and a desired statistical power of 0.99, with 7 predictors in the model, the calculated minimum sample size was 300 participants. A 10% attrition rate was also considered in estimating the final sample size. The achieved sample (n = 327) met this requirement (22).
Survey instrument
Data were collected using a demographic and occupational characteristics form and two standardized questionnaires: The Halpin and Croft Organizational Climate Questionnaire and the Presenteeism in Nursing Questionnaire.
Demographic and occupational characteristics form this study-specific form comprised two sections. The first section recorded sociodemographic information including age, gender, marital status, place of residence, and medical history. The second section collected occupational characteristics, including educational level and years of work experience.
Halpin and croft organizational climate questionnaire
Organizational climate was measured using the Halpin and Croft questionnaire (1963), which contains 32 items scored on a five-point Likert scale (1 = very low, 2 = low, 3 = moderate, 4 = high, 5 = very high). Item scores are summed to yield subscale scores and a total score.
Each of the eight subscales comprises four items (Possible subscale range = 4 - 20), and the total organizational climate score ranges from 32 to 160. The questionnaire assesses the following dimensions: Team spirit (Items 1 - 4), harassment (Items 5 - 8), intimacy (Items 9 - 12), interest (Items 13 - 16), consideration (Items 17 - 20), distancing (Items 21 - 24), influence and dynamics (Items 25 - 28), and focus on production (Items 29 - 32). Higher scores indicate a stronger perception of the corresponding climate dimension and a more positive overall organizational climate (22). The instrument has demonstrated excellent reliability and validity in Iranian healthcare settings; for example, studies among emergency medical staff reported Cronbach’s α = 0.966 and composite reliability = 0.968 (23), while other researchers have reported overall α = 0.78 (24).
Presenteeism in nursing questionnaire
Presenteeism was assessed using the 17-item presenteeism questionnaire developed and validated by Mohammadi et al. Items are rated on a five-point Likert scale (1 = never, 2 = rarely, 3 = sometimes, 4 = often, 5 = always). The instrument comprises three subscales: Incomplete cognitive presence (Items 1 - 8; range 8 - 40), incomplete emotional presence (Items 9 - 12; range 4 - 20), and incomplete behavioral presence (Items 13 - 17; range 5 - 25). Subscale scores are summed to produce a total presenteeism score (Range 17 - 85), with higher scores reflecting greater levels of presenteeism. The questionnaire’s internal consistency has been reported as acceptable (Cronbach’s α > 0.80), and content validity was confirmed by the original developers (25).
Data collection
After obtaining the necessary approvals, the questionnaire and the informed-consent form were prepared and administered electronically via Porsline (An Iranian online survey platform). The online questionnaire link was distributed through professional workgroups on Telegram and WhatsApp and the Persian app, which were used by nurses working in the selected hospitals. Participants were identified through their membership in these hospital-specific virtual groups, where the survey link and study information were posted with an invitation to participate voluntarily. Before accessing the questionnaire items, participants viewed an introductory page describing the study’s aims, ethical considerations, and confidentiality assurance. Those who agreed to participate indicated their informed consent by continuing to the questionnaire. The mean completion time per questionnaire was approximately 30 minutes. To ensure data completeness, the online questionnaire was configured with mandatory response settings for all items. Consequently, no incomplete questionnaires were collected, and no missing data imputation was necessary.
Data analysis
Descriptive statistics were computed for all study variables. Continuous variables are presented as mean ± standard deviation (SD) and median (Interquartile range, IQR) as appropriate; categorical variables are reported as frequencies and percentages. Normality of continuous variables was assessed by visual inspection of histograms and Q-Q plots and formally tested using the Shapiro - Wilk test. Because the presenteeism score was negatively skewed, the variable was natural-log transformed (Log-presenteeism) to approximate normality and stabilize variance prior to regression analyses. After log transformation, skewness (-0.317; SE = 0.136; SES = -2.34) and kurtosis (0.181; SE = 0.271; SES = 0.67) indicated a nearly symmetric and approximately normal distribution.
For data analysis, independent samples t-tests, Mann-Whitney U tests, and Pearson’s and Spearman’s correlation analyses were used as appropriate. In multivariable linear regression, all covariates identified as theoretically relevant (Age, gender, education, marital status, place of residence, and medical history) were entered simultaneously using the enter method. This approach was chosen to avoid model instability associated with automated stepwise procedures and to ensure inclusion of conceptually justified variables. Work experience was excluded from multivariable regression due to a high degree of collinearity with age. Because age and work experience were highly correlated (R = 0.87), age was retained as it theoretically reflects both biological and career-related influences on presenteeism.
Prior to conducting regression analyses, the assumptions of linearity, homoscedasticity, absence of multicollinearity, and lack of influential cases were assessed. Collinearity among independent variables was evaluated in two steps. First, pairwise correlations between continuous independent variables were examined using Spearman’s correlation coefficients. Second, multicollinearity diagnostics were performed by calculating the Variance Inflation Factor (VIF) for each predictor. All VIF values ranged between 1.00 and 1.30, indicating no multicollinearity issues. Model assumptions were further examined through standardized residuals and Cook’s distance, confirming that all assumptions were met.
All tests were two-tailed, and a P-value < 0.05 was considered statistically significant. Analyses were performed using IBM SPSS Statistics version 26.
Results
In the present study, the mean age of participants was 33.91 ± 6.75 years and their mean work experience was 9.56 ± 6.30 years. The majority of participating nurses were female (52.6%) and married (61.5%). Table 1 presents the demographic characteristics of the participants along with the comparison of organizational climate and presenteeism scores across sociodemographic subgroups.
Pearson’s correlation analysis (Performed on log-transformed presenteeism scores to correct for non-normality) indicated a positive correlation between organizational climate and nurses’ age (R = 0.152, P-value = 0.006), while no significant correlation was observed with work experience (R = 0.084, P-value = 0.128). Moreover, log-transformed presenteeism was positively correlated with nurses’ age (R = 0.125, P-value = 0.024) but not with work experience (P > 0.05).
Correlation between organizational climate and presenteeism orientation scale score
Cronbach’s alpha for the Organizational Climate scale was α = 0.72 and for the Presenteeism scale α = 0.84, both exceeding the conventional threshold of 0.70, indicating acceptable to good internal consistency. Spearman’s correlation analysis revealed a weak but statistically significant negative correlation between organizational climate and nurses’ presenteeism (rs = -0.156, P-value = 0.005). Descriptions of the dimensions of the main variables are reported in Table 2.
A multivariable linear regression was performed with log-transformed presenteeism as the dependent variable (n = 327). The overall model was significant (F (7, 319) = 4.93, P < 0.001) and explained 7.8% of the variance in log-presenteeism (R² = 0.098, adjusted R² = .078). Organizational climate was a significant negative predictor of log-presenteeism, while age was a significant positive predictor, indicating that while organizational climate and age were statistically significant predictors, the overall explanatory power of the model was modest. This suggests that other unmeasured factors may play a larger role in predicting nurses’ presenteeism; other covariates were not significant (Table 3). Diagnostics indicated no problematic multicollinearity (VIFs ≈ 1.0), no influential cases (Maximum Cook’s D = 0.057), and standardized residuals within acceptable bounds (Min = -3.89, max = 2.40).
Higher organizational climate scores were independently associated with slightly lower presenteeism (Approximately 0.5% decrease in the original scale per 1-unit increase in organizational climate), while older age was associated with slightly higher presenteeism; effect sizes were small.
|
Table 1. Comparison of organizational climate and presenteeism scores across sociodemographic characteristics of nurses (N = 327)
 N = Frequency; % = Percentage; OC = Organizational Climate; BSN = Bachelor of Science in Nursing; MSN = Master of Science in Nursing; SD = Standard Deviation; IQR = Interquartile Range * Independent t-test; ** Mann-Whitney U test Table 2. Descriptive profile of organizational climate domains and presenteeism in nurses (N = 327)  OC = Organizational Climate; Inc = Incomplete; Min = Minimum; Max = Maximum |
|
Table 3. Multivariable linear regression predicting log-presenteeism (N = 327)
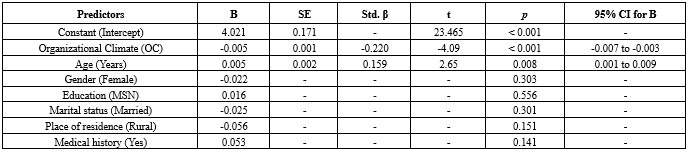 Dependent variable = Natural-log of presenteeism. SE = Standard Error; Std β = Standardized Beta For categorical variables, the following groups were used as references: Male (Gender), BSN (Education), single (Marital status), urban (Residence), and no medical history (Health status) |
Discussion
Organizational climate and presenteeism among nurses in this study were reported at moderate levels. The present study found that higher organizational climate scores were associated with lower levels of nurse presenteeism. In other words, each one-unit increase in the overall organizational climate score predicted an approximately 0.5% reduction in nurses’ presenteeism, although the effect size was small. This finding is consistent with several studies. Jing et al. (2026), in an international longitudinal study, showed that ethical leadership had a reducing effect on nurse presenteeism and that part of this relationship was mediated by organizational climate and professional identity (25). Mansour et al. (2022) found that psychological safety climate (One facet of organizational climate) significantly reduced presenteeism in nurses by attenuating the intensity of workload (26). Wang et al. (2024) reported that the greater the perceived organizational support (POS) among nurses, the lower the frequency of presenteeism and its associated harms (27).
In this study, nurses assigned the highest organizational-climate scores to the dimensions of “Intimacy” and “team spirit,” which reflects the importance of close interpersonal relationships and team cohesion in the nursing work environment (28). Organizational intimacy, defined as the proximity, solidarity, and tendency of team members to be together, has been shown to be associated with increased team participation, positive organizational behavior, and job satisfaction (29). Moreover, studies indicate that work settings in which nurses feel supported, valued, and perceive organizational attention to their participation and welfare lead to improved job satisfaction and better mental health among nurses (14,30). Consistent with these findings, a positive perception of working conditions (Including work-life balance and coworker support) can help prevent stress-induced presenteeism in nurses. In addition, reviews of positive nursing work environments have identified the “communication climate (Team spirit)” as one of the key components of the workplace (31).
Mohammadi et al., in a qualitative study in Iran, examined the notion of “nurses without a nurse,” showing that when the organizational climate is not support-oriented, managers may neglect to acknowledge the necessity of nurses’ attendance when ill. Nurses reported that managers sometimes tell them, “We cannot sacrifice patients because of your absence; you are a nurse and must be at your post!” This kind of undermining organizational climate, where managers encourage physical attendance even under adverse conditions, is a clear manifestation of presenteeism (32). Overall, a favorable organizational climate, by fostering a sense of belonging and mutual support among staff, reduces undesirable behaviors such as presenteeism (26). Moreover, a recent systematic review by Gerlach et al. (2024) emphasized that improving working conditions and promoting a supportive organizational culture and effective management can mitigate the negative effects of presenteeism among nurses (33).
In short, the broader body of evidence indicates a negative relationship between the quality of organizational climate and the prevalence of presenteeism, a pattern that is echoed across multiple contemporary studies. From the perspective of Social Exchange Theory, when employees perceive that the organization cares for and supports their well-being, they reciprocate with loyalty and a sense of responsibility; thus, high organizational support can strengthen commitment in ways that manifest as positive work behaviors such as reduced presenteeism (34,35). Likewise, according to Conservation of Resources theory, a positive organizational climate (Especially one characterized by psychological safety) constitutes an important job resource that helps employees preserve their psychological and physical resources and prevents fatigue or occupational burnout. Shafiee Sabet et al. (2023) reported that most nurses did not perceive their shift schedules as aligned with their preferences and recommended that managers take steps to reduce presenteeism and enhance nurses’ resilience (19). Mansour et al. (2022), drawing on the same theoretical perspective, showed that a psychological safety climate, by reducing job stressors, increases nurses’ capacity to cope with heavy workloads and thereby prevents presenteeism (26).
This is one of the first studies to examine organizational climate and presenteeism among nurses in Iran. The present study has several important strengths, including an adequate sample size (n = 327) and a favorable response rate (81.3%), use of standardized and locally validated questionnaires with reported reliability, adherence to STROBE reporting guidelines, and rigorous statistical analyses, such as logarithmic transformation to normalize the presenteeism variable, along with diagnostic model checks and control of multiple background covariates, all of which contribute to the study’s internal validity.
Nevertheless, several limitations must be acknowledged when interpreting our findings. First, the cross-sectional design precludes causal inference. Second, convenience sampling from a limited number of centers and the web-based distribution may produce a local/selection bias and limit generalizability to other regions or to nurses with lower digital access or different working conditions. Third, exclusive reliance on self-report measures increases the risk of common-method variance, recall error, and social-desirability bias. Fourth, the regression model accounted for only a small proportion of the variance in presenteeism (Adjusted R² = 0.078), indicating that the included predictors-mainly demographic and organizational climate variables-were not strong determinants of presenteeism. This suggests that additional organizational and job-related factors (e.g., workload, shift patterns, or staffing adequacy) likely play a more substantial role and should be examined in future research. Taken together, these limitations argue for cautious interpretation of the results.
Based on the findings of this study, future research should explore the causal relationship between organizational climate and presenteeism using longitudinal or experimental designs. It is recommended that future studies examine potential mediating and moderating variables such as perceived organizational support, individual resilience, and organizational commitment to better understand the mechanisms linking climate to presenteeism.
Conclusion
The present study found that a more positive organizational climate was associated with lower levels of presenteeism among nurses, although the effect size was modest. These findings suggest actionable managerial strategies that healthcare organizations can adopt to mitigate presenteeism and improve care quality, for example, flexible scheduling and self-rostering, ensuring adequate staffing and equitable workload redistribution, implementing employee psychological-support services, training managers in supportive leadership and conflict resolution, and establishing formal peer-support and clear absence policies.
Acknowledgement
This study was approved by the Student Research Committee of Golestan University of Medical Sciences. The authors thank the Vice-Chancellor for Research and Technology of Golestan University of Medical Sciences for their support.
Funding sources
None.
Ethical statement
The study protocol was approved by the Ethical Review Board of Golestan University of Medical Sciences (IR.GOUMS.REC.1404.224). The study was conducted in accordance with the principles of the Declaration of Helsinki. All participants provided written informed consent after being informed about the study aims, procedures, potential risks, and benefits. Participation was voluntary; participants were explicitly informed that they could refuse to participate or withdraw at any time without penalty or loss of benefits to which they were otherwise entitled. Participant confidentiality was maintained: Data were anonymized/coded and stored securely with access restricted to authorized study personnel.
Conflicts of interest
None.
Author contributions
S. K. and R. J.: Conceptualization; S. K., L. J., A. S., and R. J.: Methodology; A. S. and S. K.: Resources; R. J. and S. K.: Writing-Original draft preparation; J. D. and R. J.: Writing-Review and Editing; L. J. and A. S.: Supervision; R. J.: Project administration.
Data availability statement
All data analyzed during this study are included in this published article. Additional de-identified participant-level data may be made available from the corresponding author upon reasonable request, subject to review and approval by the study authors and applicable institutional policies.
Use of Artificial Intelligence
The authors acknowledge the contribution of ChatGPT (OpenAI) in translating and paraphrasing portions of this manuscript.
Type of study: Original Article |
Subject:
Nursing
References
1. Mallagoli ISS, Matias AB, da Silva EP, Oliveira MAN, Sampaio AN, Belasco AGS. The association between work capacity, quality of life, and organizational climate among nurses. Rev Bras Med Trab. 2025;23(2):e20251373. [View at Publisher] [DOI] [PMID] [Google Scholar]
2. Mohammadi MM, Dehghan Nayeri N, Varaei S, Rasti A. Exploring the concept of presenteeism in nursing: A hybrid concept analysis. Int J Nurs Knowl. 2021;32(3):166-76. [View at Publisher] [DOI] [PMID] [Google Scholar]
3. Rainbow JG, Steege LM. Presenteeism in nursing: An evolutionary concept analysis. Nurs Outlook. 2017;65(5):615-23. [View at Publisher] [DOI] [PMID] [Google Scholar]
4. Zedeck SE. APA handbook of industrial and organizational psychology, Vol 1: Building and developing the organization: American Psychological Association; 2011. P. xxxiv-686 [View at Publisher] [DOI] [Google Scholar]
5. Hammer LB, Truxillo DM, Bodner T, Pytlovany AC, Richman A. Exploration of the impact of organisational context on a workplace safety and health intervention. Work Stress. 2019;33(2):192-210. [View at Publisher] [DOI] [Google Scholar]
6. Kiptulon EK, Elmadani M, Limungi GM, Simon K, Tóth L, Horvath E, et al. Transforming nursing work environments: the impact of organizational culture on work-related stress among nurses: a systematic review. BMC Health Serv Res. 2024;24(1):1526. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. Billah SMB, Saquib N, Zaghloul MS, Rajab AM, Aljundi SMT, Almazrou A, et al. Unique expatriate factors associated with job dissatisfaction among nurses. Int Nurs Rev. 2021;68(3):358-64. [View at Publisher] [DOI] [PMID] [Google Scholar]
8. Zhang L, Han L, Liang X, Wang R, Fan H, Jia Y, et al. The relationship between transformational leadership and work engagement among intensive care unit nurses: the mediating function of organizational climate. BMC Nurs. 2025;24(1):398. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Abou Hashish EA. Relationship between ethical work climate and nurses' perception of organizational support, commitment, job satisfaction and turnover intent. Nurs Ethics. 2017;24(2):151-66. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. Fujino Y. Health management of workers with presenteeism is a new challenge in occupational health. J UOEH. 2018;40(3):225-30. [View at Publisher] [DOI] [PMID] [Google Scholar]
11. Silva AF, Robazzi MLdCC, Dalri RdCdMB, Silveira-Monteiro CA, Mendes AMOC. Presenteeism in multiprofessional team workers in the Adult Intensive Care Unit. Rev Bras Enferm. 2019;72(suppl 1):96-104. [View at Publisher] [DOI] [PMID] [Google Scholar]
12. Pereira F, Querido A, Verloo H, Bieri M, Laranjeira C. Consequences of Nurse Presenteeism in Switzerland and Portugal and Strategies to Minimize It: A Qualitative Study. Healthcare. 2022;10(10):1871. [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Alameddine M, Clinton M, Bou-Karroum K, Richa N, Doumit MAA. Factors Associated With the Resilience of Nurses During the COVID-19 Pandemic. Worldviews Evid Based Nurs. 2021;18(6):320-31. [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Rainbow JG, Drake DA, Steege LM. Nurse Health, Work Environment, Presenteeism and Patient Safety. West J Nurs Res. 2020;42(5):332-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Demerouti E, Le Blanc PM, Bakker AB, Schaufeli WB, Hox J. Present but sick: a three‐wave study on job demands, presenteeism and burnout. Career Dev Int. 2009;14(1):50-68. [View at Publisher] [DOI] [Google Scholar]
16. Gerlach M, Blozik E, Meichtry A, Hägerbäumer M, Kilcher G, Golz C. Factors of presenteeism and its association with detrimental effects among employees in Switzerland working in different sectors - a cross-sectional study using a multi-item instrument. Int Arch Occup Environ Health. 2024;97(7):767-78. [View at Publisher] [DOI] [PMID] [Google Scholar]
17. Hubbell AP, Chory‐Assad RM. Motivating factors: perceptions of justice and their relationship with managerial and organizational trust. Commun Stud. 2005;56(1):47-70. [View at Publisher] [DOI] [Google Scholar]
18. Majeed M, Fatima T. Impact of exploitative leadership on psychological distress: A study of nurses. J Nurs Manag. 2020;28(7):1713-24. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Shafiee Sabet M, Vahedi S, Bahramnezhad F, Dehghan Nayeri N. Investigating the relationship between presentism and resilience of critical care nurses of hospitals affiliated with Tehran University of Medical Sciences. Payesh J. 2023;22(6):727-35. [View at Publisher] [DOI] [Google Scholar]
20. Vandenbroucke JP, von Elm E, Altman DG, Gøtzsche PC, Mulrow CD, Pocock SJ, et al. Strengthening the Reporting of Observational Studies in Epidemiology (STROBE): Explanation and elaboration. Int J Surg. 2014;12(12):1500-24. [View at Publisher] [DOI] [PMID] [Google Scholar]
21. Pavlovic IJ. The Effect of Organizational Climate on Presenteeism as Moderated by Employee Personality. [doctoral dissertation]. Minneapolis (MN): Walden University; 2022. [View at Publisher] [Google Scholar]
22. Faul F, Erdfelder E, Lang A-G, Buchner A. G*Power 3: A flexible statistical power analysis program for the social, behavioral, and biomedical sciences. Behav Res Methods. 2007;39(2):175-91. [View at Publisher] [DOI] [PMID] [Google Scholar]
23. Tahmasebi Ghorrabi A, Aghaei HA, Sabzi AR, Jahanbani E, Kaid khordeh M, Zahiri M. Validity and reliability of the Persian edition of Halpin and Craft's Organizational Climate Questionnaire: A study among emergency medical center workers in Ahvaz, Iran. J Health. 2023;11(3):1-9. [View at Publisher] [DOI] [Google Scholar]
24. Pazhouhan A, Safari Y, Naderi N. Evaluating the predictability of organizational health by the eight dimensions of organizational climate; A case of study: Kermanshah University of Medical Sciences. Manage Strat Health Syst. 2023;8(1):60-76. [View at Publisher] [DOI] [Google Scholar]
25. Jing J-T, Qiu H-N, Fu Y-K, Ma Z-Y, Liu D-R, Liu J,et al. The impact and mechanisms of ethical leadership on nurse presenteeism: A multicenter longitudinal study. Nurs Outlook. 2026;74(1):102602. [View at Publisher] [DOI] [PMID] [Google Scholar]
26. Mansour S, Faisal Azeem M, Dollard M, Potter R. How Psychosocial Safety Climate Helped Alleviate Work Intensification Effects on Presenteeism during the COVID-19 Crisis? A Moderated Mediation Model. Int J Environ Res Public Health. 2022;19(20):13673. [View at Publisher] [DOI] [PMID] [Google Scholar]
27. Wang T, Qin H, Zhang Z, Qin Y. The moderating effect of perceived organizational support on presenteeism related to the inclusive leadership. BMC Nurs. 2024;23:139. [View at Publisher] [DOI] [PMID] [Google Scholar]
28. Hahm SY, Gu M, Sok S. Influences of communication ability, organizational intimacy, and trust among colleagues on job satisfaction of nurses in comprehensive nursing care service units. Front Public Health. 2024;12:1354972. [View at Publisher] [DOI] [PMID] [Google Scholar]
29. Larsman P, Pousette A, Törner M. The impact of a climate of perceived organizational support on nurses' well-being and healthcare-unit performance: A longitudinal questionnaire study. J Adv Nurs. 2024;80(12):4921-32. [View at Publisher] [DOI] [PMID] [Google Scholar]
30. Vaz AC, Vermelho M, Silva M, Costa P, Dinis SM, Severino S, et al. Presenteeism and Burnout in Nurses: A Review of the Literature. Encyclopedia. 2025;5(3):93. [View at Publisher] [DOI] [Google Scholar]
31. Emiralioğlu R, Sönmez B. Positive Work Environment in Nursing: Components and Strategies. J Educ Res Nurs. 2025;22(2):156-60. [View at Publisher] [DOI] [Google Scholar]
32. Mohammadi MM, Nayeri ND, Varaei S, Rasti A. The nurse without a nurse: the antecedents of presenteeism in nursing. BMC Nursing. 2021;20(1):143. [View at Publisher] [DOI] [PMID] [Google Scholar]
33. Gerlach M, Hahn S, Rossier C, Geese F, Hamers J, Backhaus R. Presenteeism among nurses: An integrative review. Int J Nurs Stud Adv. 2024;7:100261. [View at Publisher] [DOI] [PMID] [Google Scholar]
34. Khan MAS, Du J, Anwar F, Khan H, Shahzad F, Qalati SA. Corporate Social Responsibility and the Reciprocity Between Employee Perception, Perceived External Prestige, and Employees' Emotional Labor. Psychol Res Behav Manag. 2021;14:61-75. [View at Publisher] [DOI] [PMID] [Google Scholar]
35. Safy-Godineau F, Fall A, Carassus D. The Influence of Perceived Organizational Support and Organizational Commitment on Absenteeism in the Local Public Sector. Gest manag public. 2021;9(2):79-97. [View at Publisher] [DOI] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
